Key Updates for Week 21, ending May 23, 2020
Nationally, levels of influenza-like illness (ILI) and COVID-19-like illness (CLI) and the percentage of specimens testing positive for SARS-CoV-2, the virus that causes COVID-19, continue to decline or remain stable. Mortality attributed to COVID-19 also decreased compared to last week but remains elevated above baseline and may increase as additional death certificates are processed.
Virus
Public Health, Commercial and Clinical Laboratories
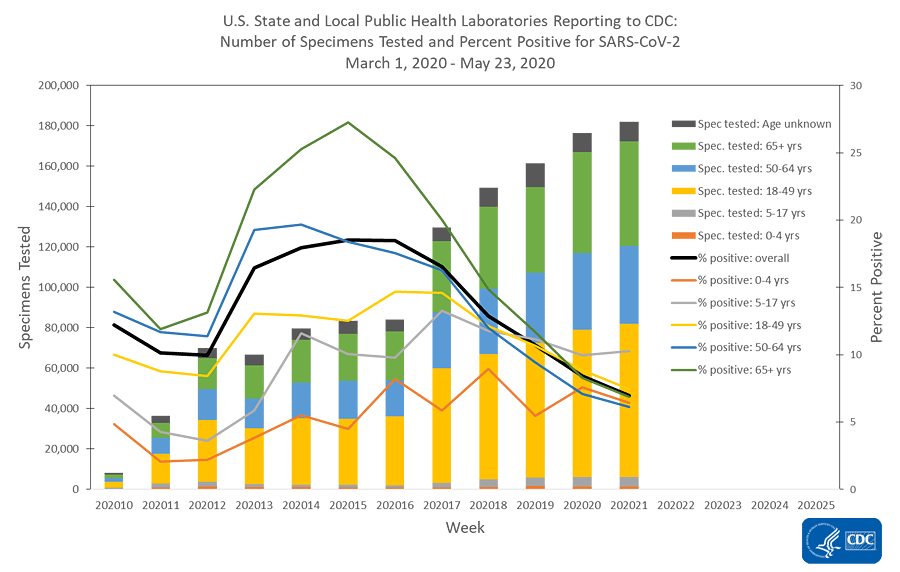
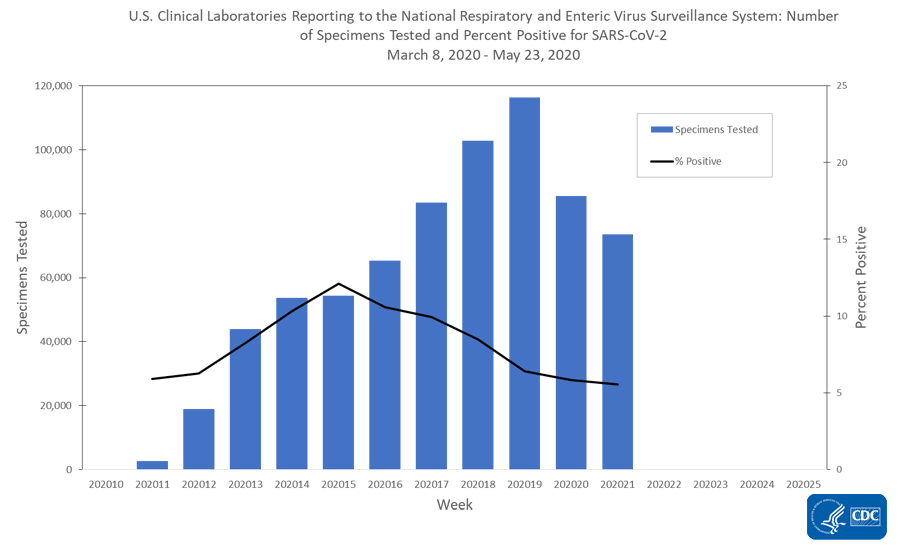
The national percentage of respiratory specimens testing positive for SARS-CoV-2 at public health, clinical and commercial laboratories decreased from week 20 to week 21; however, percent positivity increased slightly in two regions. National percentages by type of laboratory:
- Public health laboratories – decreased from 8.4% during week 20 to 7.0% during week 21;
- Clinical laboratories – decreased from 6.3% during week 20 to 5.6% during week 21;
- Commercial laboratories – decreased from 7.8 % during week 20 to 6.9% during week 21.
Outpatient and Emergency Department Visits
Outpatient Influenza-Like Illness Network (ILINet) and National Syndromic Surveillance Program (NSSP)
Two surveillance indicators are being used to track outpatient or emergency department (ED) visits for illness with symptoms compatible with COVID-19.
- Nationally, the percentages of visits for ILI and CLI decreased or remained stable at low levels, compared to last week. Levels of ILI are below baseline nationally for the sixth week and in all 10 surveillance regions for the past four to seven weeks.
Recent changes in health care seeking behavior, including increasing use of telemedicine, recommendations to limit emergency department (ED) visits to severe illnesses, and increased practice of social distancing, are likely affecting data reported from both networks, making it difficult to draw conclusions at this time. Tracking these systems moving forward will give additional insight into illness related to COVID-19.
Severe Disease
Hospitalizations
Cumulative COVID-19-associated hospitalization rates since March 1, 2020, are updated weekly. The overall cumulative COVID-19 hospitalization rate is 73.3 per 100,000, with the highest rates in people aged 65 years and older (229.7 per 100,000) and 50-64 years (113.4 per 100,000).
Mortality
Based on death certificate data, the percentage of deaths attributed to pneumonia, influenza or COVID-19 (PIC) decreased from 15.9% during week 20 to 9.8% during week 21 but remained above baseline. This is the fifth week of a declining percentage of deaths due to PIC, but this percentage may change as more death certificates are processed, particularly for recent weeks.
All data are preliminary and may change as more reports are received.
A description of the surveillance systems summarized in COVIDView, including methodology and detailed descriptions of each data component, is available on the surveillance methods page.
Key Points
- Nationally, the percentages of laboratory specimens testing positive for SARS-CoV-2 with a molecular assay decreased compared to last week; however, there are two developments in particular worth noting:
- The percent positivity increased slightly in two HHS surveillance regions (Regions 4 [the southeast] and 10 [the Pacific northwest]).
- While the number of specimens from children <18 years of age tested is low (<5% of all specimens tested in public health and commercial laboratories), the percentage testing positive for SARS-CoV-2 in this age group has either trended upward or remained relatively stable in recent weeks. Other age groups have seen declines in percent positivity during the same time period.
- Nationally, visits to outpatient providers and emergency departments (EDs) for illnesses with symptoms consistent with COVID-19 continued to decline or remain stable at low levels. Outpatient ILI visits are below baseline nationally and in all regions of the country.
- The decrease in the percentage of people presenting for care with ILI and CLI may be due to a decline in COVID-19 illness, which could be in part a result of widespread adoption of social distancing, in addition to decreases in healthcare seeking behavior.
- There has been very little influenza virus activity in recent weeks.
- The overall cumulative COVID-19 associated hospitalization rate is 73.3 per 100,000, with the highest rates in people 65 years of age and older (229.7 per 100,000) followed by people 50-64 years (113.4 per 100,000). Hospitalization rates are cumulative and will increase as the COVID-19 pandemic continues.
- This week’s report presents additional information on racial and ethnic disparities among reported COVID-19 hospitalizations. Non-Hispanic Black and non-Hispanic American Indian/Alaska Native populations have rates approximately 4.5 times that of non-Hispanic Whites, while Hispanic/Latinos have a rate approximately 3.5 times that of non-Hispanic Whites.
- Cumulative hospitalization rates for COVID-19 in adults (18-64 years) at this time are higher than cumulative end-of-season hospitalization rates for influenza over each of the past 5 influenza seasons.
- For people 65 years and older, current cumulative COVID-19 hospitalization rates are within ranges of cumulative influenza hospitalization rates observed at comparable time points* during recent influenza seasons.
- For children (0-17 years), cumulative COVID-19 hospitalization rates are much lower than cumulative influenza hospitalization rates at comparable time points* during recent influenza seasons.
- Based on death certificate data, the percentage of deaths attributed to pneumonia, influenza or COVID-19 (PIC) decreased from 15.9% during week 20 to 9.8% during week 21 but remained above baseline. This is the fifth week during which a declining percentage of deaths due to PIC has been recorded. The percentage remains above the epidemic threshold, and is now similar to what has been observed at the peak of some influenza seasons. The percentage may change as additional death certificates for deaths during recent weeks are processed.
*Number of weeks since 10% of specimens tested positive for SARS-CoV-2 and influenza, respectively.
The number of specimens tested for SARS-CoV-2 using a molecular assay and reported to CDC by public health laboratories and a subset of clinical and commercial laboratories in the United States are summarized below. All laboratories are performing primary diagnostic functions; therefore, the percentage of specimens testing positive across laboratory types can be used to monitor overall trends in COVID-19 activity. As the outbreak progresses, it is possible that different types of laboratories will take on different roles, and the data interpretation may need to change. The lower percentage of specimens testing positive in clinical laboratories compared to public health and commercial laboratories may be influenced by COVID-19 activity in areas with reporting laboratories and by larger proportions of specimens obtained from children tested in these laboratories.
| Summary of Laboratory Testing Results Reported to CDC* | Week 21 (May 17 – May 23, 2020) | Cumulative since March 1, 2020 |
|---|---|---|
| No. of specimens tested | 1,171,546 | 8,762,465 |
| Public Health Laboratories | 182,009 | 1,227,717 |
| Clinical Laboratories | 72,256 | 740,691 |
| Commercial Laboratories | 917,281 | 6,794,057 |
| No. of positive specimens (%) | 79,898 (6.8%) | 1,145,733 (13.1%) |
| Public Health Laboratories | 12,702 (7.0%) | 153,579 (12.5%) |
| Clinical Laboratories | 4,041 (5.6%) | 60,520 (8.2%) |
| Commercial Laboratories | 63,155 (6.9%) | 931,634 (13.7%) |
* Commercial and clinical laboratory data represents select laboratories and does not capture all tests performed in the United States.
Public Health Laboratories
View Data Table
Clinical Laboratories
View Data Table
Commercial Laboratories
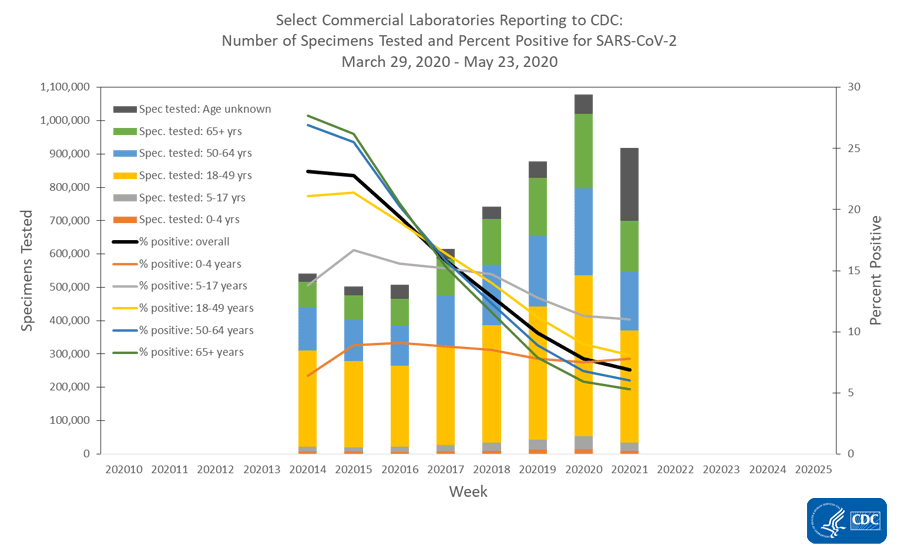
* Commercial laboratories began testing for SARS-CoV-2 in early March, but the number and geographic distribution of reporting commercial laboratories became stable enough to calculate a weekly percentage of specimens testing positive as of March 29, 2020.
View Data Table
Outpatient/Emergency Department Illness
Two syndromic surveillance systems are being used to monitor trends in outpatient and emergency department visits that may be associated with COVID-19 illness. Each system monitors a slightly different syndrome, and together these systems provide a more comprehensive picture of mild to moderate COVID-19 illness than either would individually. Both systems are currently being affected by recent changes in healthcare seeking behavior, including increased use of telemedicine, compliance with recommendations to limit emergency department (ED) visits to severe illnesses, and increased practice of social distancing. These changes affect the numbers of people seeking care in the outpatient and ED settings and their reasons for doing so.
ILINet
The U.S. Outpatient Influenza-like Illness Surveillance Network (ILINet) provides data on visits for influenza-like illness (ILI) (fever [≥100○F] and cough and/or sore throat) to approximately 2,600 primary care providers, emergency departments and urgent care centers in all 50 states, Puerto Rico, the District of Columbia and the U.S. Virgin Islands. Mild COVID-19 illness presents with symptoms similar to ILI, so ILINet is being used to track trends of mild to moderate COVID-19 illness and allows for comparison with prior influenza seasons.
Nationwide during week 21, 1.0% of patient visits reported through ILINet were due to ILI. This percentage is low and below the national baseline of 2.4% and represents the ninth week of decline after three weeks of increase beginning in early March. Compared to week 20, the percentage of visits for ILI in week 21 decreased slightly among all age groups. Nationally, laboratory-confirmed influenza activity as reported by clinical laboratories is at levels usually seen during summer months which, along with changes in healthcare seeking behavior and the impact of social distancing, is likely contributing to the low level of ILI activity.
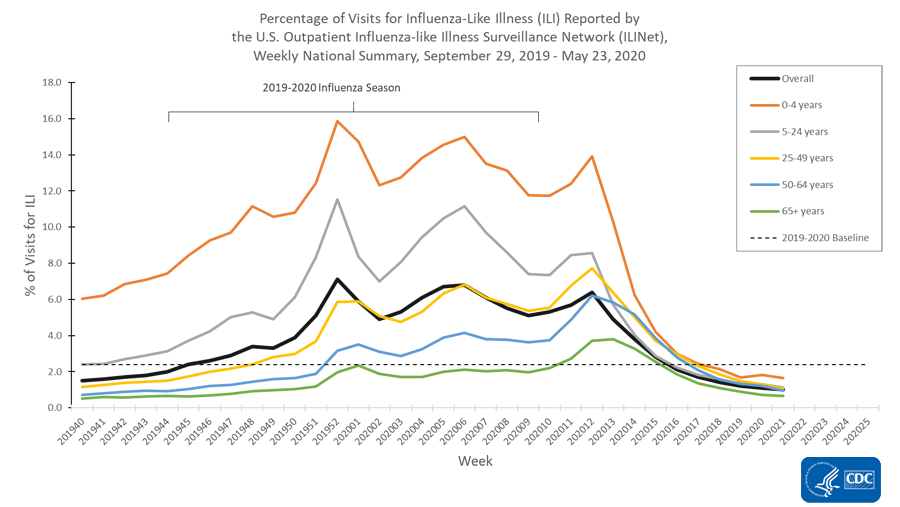
* Age-group specific percentages should not be compared to the national baseline.
On a regional level, the percentage of outpatient visits for ILI ranged from 0.4% to 1.5% during week 21. Compared to week 20, the percent of outpatient visits for ILI decreased or remained stable at low levels in all ten regions and all regions are below their region-specific baselines.
Note: In response to the COVID-19 pandemic, new sites will be enrolled in ILINet throughout the summer. This will result in an increase in patient visits and the percentage of visits for ILI may change in comparison to previous weeks. During week 21, new sites were added in Regions 1, 4, and 6. While these regions remain below baseline levels for ILI, these system changes should be kept in mind when drawing conclusions from these data. Any changes in ILI due to changes in respiratory virus circulation will be highlighted here.
Overall Percentage of Visits for ILI | Age Group ILI Data
ILI Activity Levels
Data collected in ILINet are used to produce a measure of ILI activity for all 50 states, Puerto Rico, the District of Columbia and New York City. The mean reported percentage of visits due to ILI for the current week is compared to the mean reported during non-influenza weeks, and the activity levels correspond to the number of standard deviations below, at or above the mean.
The number of jurisdictions at each activity level during week 21 and the change compared to the previous week are summarized in the table below and shown in the following maps. The decreasing percentage of visits for ILI described above are reflected in this week’s ILI activity levels.
| Activity Level | Number of Jurisdictions | |
| Week 21 (Week ending May 23, 2020) | Compared to Previous Week | |
| Very High | 0 | No change |
| High | 1 | No change |
| Moderate | 0 | -2 |
| Low | 2 | No change |
| Minimal | 49 | +1 |
| Insufficient Data | 2 | +1 |
*Data collected in ILINet may disproportionally represent certain populations within a state and may not accurately depict the full picture of influenza activity for the whole state. Differences in the data presented here by CDC and independently by some state health departments likely represent differing levels of data completeness with data presented by the state likely being the more complete.
National Syndromic Surveillance Program (NSSP): Emergency Department (ED) Visits
NSSP is a collaboration among CDC, federal partners, local and state health departments and academic and private sector partners to collect, analyze and share electronic patient encounter data received from multiple healthcare settings. To track trends of potential COVID-19 visits, visits for COVID-19-like illness (CLI) (fever and cough or shortness of breath or difficulty breathing or presence of a coronavirus diagnosis code) and ILI to a subset of emergency departments in 47 states are being monitored.
Nationwide during week 21, 2.2% of emergency department visits captured in NSSP were due to CLI and 0.7% were due to ILI. This is the ninth week of decline in the percentage of visits for ILI and the seventh week of declining percentage of visits for CLI. Compared to week 20, all 10 HHS regions had declining percentages of visits for CLI during week 21; all 10 regions also had declining or stable percentages of visits for ILI.
Additional information about medically attended outpatient and emergency department visits for ILI and CLI: Surveillance Methods
Hospitalizations
The COVID-19-Associated Hospitalization Surveillance Network (COVID-NET) conducts population-based surveillance for laboratory-confirmed COVID-19-associated hospitalizations in select counties participating in the Emerging Infections Program (EIP) and the Influenza Hospitalization Surveillance Project (IHSP).
A total of 23,811 laboratory-confirmed COVID-19-associated hospitalizations were reported by sites between March 1, 2020, and May 23, 2020. The overall cumulative hospitalization rate was 73.3 per 100,000 population. Among the 0-4 years, 5-17 years, 18-49 years, 50-64 years, and ≥ 65 years age groups, the highest rate of hospitalization is among adults aged 65 years (229.7 per 100,000), followed by adults aged 50-64 years (113.4 per 100,000) and adults aged 18-49 years (41.0 per 100,000).
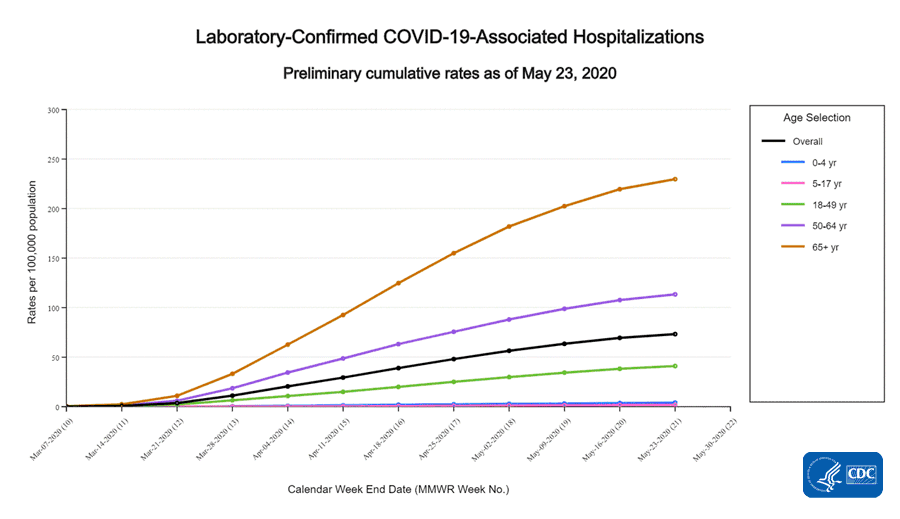
Within the 18-49 years and ≥ 65 years age groups, the hospitalization rates increased with increasing age.
| Age Group | Cumulative Rate per 100,000 Population |
|---|---|
| Overall | 73.3 |
| 0-4 years | 4.1 |
| 5-17 years | 1.9 |
| 18-49 years | 41.0 |
18-29 years | 20.1 |
30-39 years | 40.7 |
40-49 years | 68.5 |
| 50-64 years | 113.4 |
| 65+ years | 229.7 |
65-74 years | 167.6 |
75-84 years | 276.2 |
85+ years | 426.7 |
Among the 23,811 laboratory-confirmed COVID-19-associated hospitalized cases, 19,775 (83%) had information available on race and ethnicity while collection of race and ethnicity data was still pending for 4,036 (17%) cases. Of the 19,775 cases with race and ethnicity data, 35.6% were non-Hispanic White, 34.1% were non-Hispanic Black, 17.9% were Hispanic/Latino, 4.5% were non-Hispanic Asian/Pacific Islander, 1.4% were non-Hispanic American Indian/Alaska Native, 0.2% were multiple race, and 6.3% had unknown race. In comparison, the COVID-NET catchment area population includes 58.8% non-Hispanic White, 17.7% non-Hispanic Black, 14.0% Hispanic/Latino, 8.8% non-Hispanic Asian/Pacific Islander, and 0.7% non-Hispanic American Indian/Alaska Native residents. Additional data on race and ethnicity by age are available.
COVID-19-associated hospitalization rates by race and ethnicity are calculated using hospitalized COVID-NET cases with known race and ethnicity for the numerator and NCHS bridged-race population estimates for the denominator. Rates are adjusted to account for differences in age distributions within race and ethnicity strata in the COVID-NET catchment area; the age strata used for the adjustment include 0-17, 18-49, 50-64, 75-84, and ≥85 years. Age-adjusted hospitalization rates are highest in non-Hispanic American Indian/Alaska Native and non-Hispanic Black populations, followed by Hispanic/Latino. Non-Hispanic Black and non-Hispanic American Indian/Alaska Native populations have a rate approximately 4.5 times that of non-Hispanic Whites, while Hispanic/Latinos have a rate approximately 3.5 times that of non-Hispanic Whites.
Among 5,187 hospitalized adults with information on underlying medical conditions, 91.7% had at least one reported underlying medical condition, the most commonly reported were hypertension, obesity, chronic metabolic disease, and cardiovascular disease.
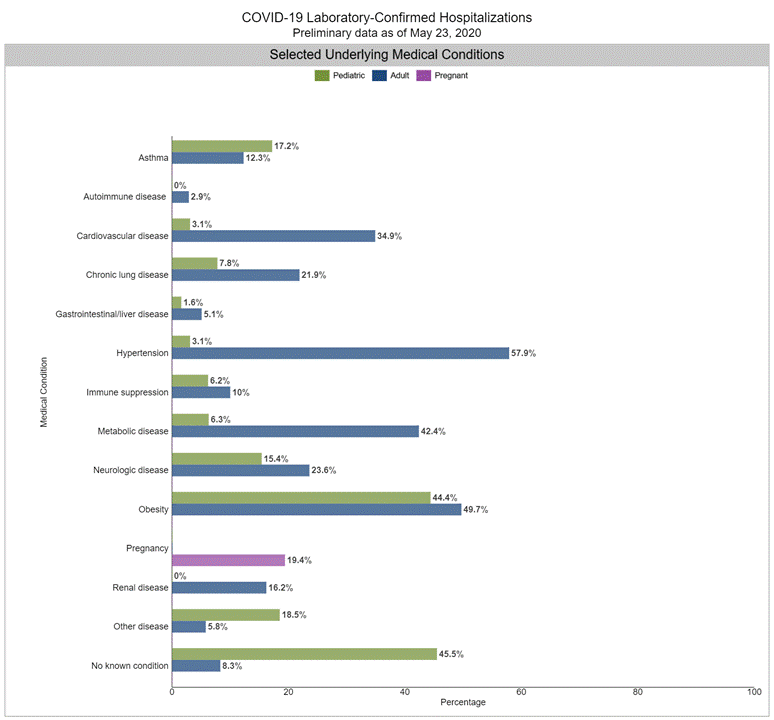
Additional hospitalization surveillance information: Surveillance Methods | Additional rate data | Additional demographic and clinical data
Mortality Surveillance
The National Center for Health Statistics (NCHS) collects death certificate data from vital statistics offices for all deaths occurring in the United States. Based on death certificate data available on May 28, 2020, 9.8% of all deaths occurring during the week ending May 23, 2020 (week 21) were due to pneumonia, influenza or COVID-19 (PIC). This is the fifth week of a declining percentage of deaths due to PIC; however, the percentage remains above the epidemic threshold of 6.4% for week 21. Data for recent weeks are incomplete, and the PIC percentage may increase as more death certificates representing deaths during these weeks are processed.
Weekly mortality surveillance data include a combination of machine coded and manually coded causes of death collected from death certificates. Percentages of deaths due to PIC are higher among manually coded records than more rapidly available machine coded records. Due to the additional time needed for manual coding, the initially reported PIC percentages may be lower than percentages calculated from final data.
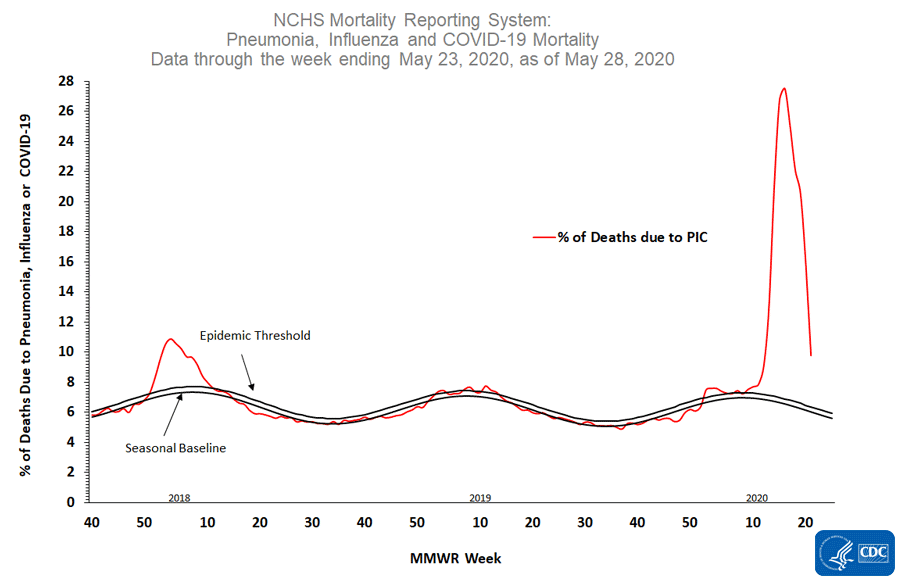
*Data during recent weeks are incomplete because of the lag in time between when the death occurred and when the death certificate is completed, submitted to NCHS and processed for reporting purposes.
View Data Table
Additional NCHS mortality surveillance information: Surveillance Methods | Provisional Death Counts for COVID-19
More Information
View Page In: 49 Pages, 3 MB















